Ankle Instability After Repeated Sprains: When ATFL Injury Needs Specialist Care
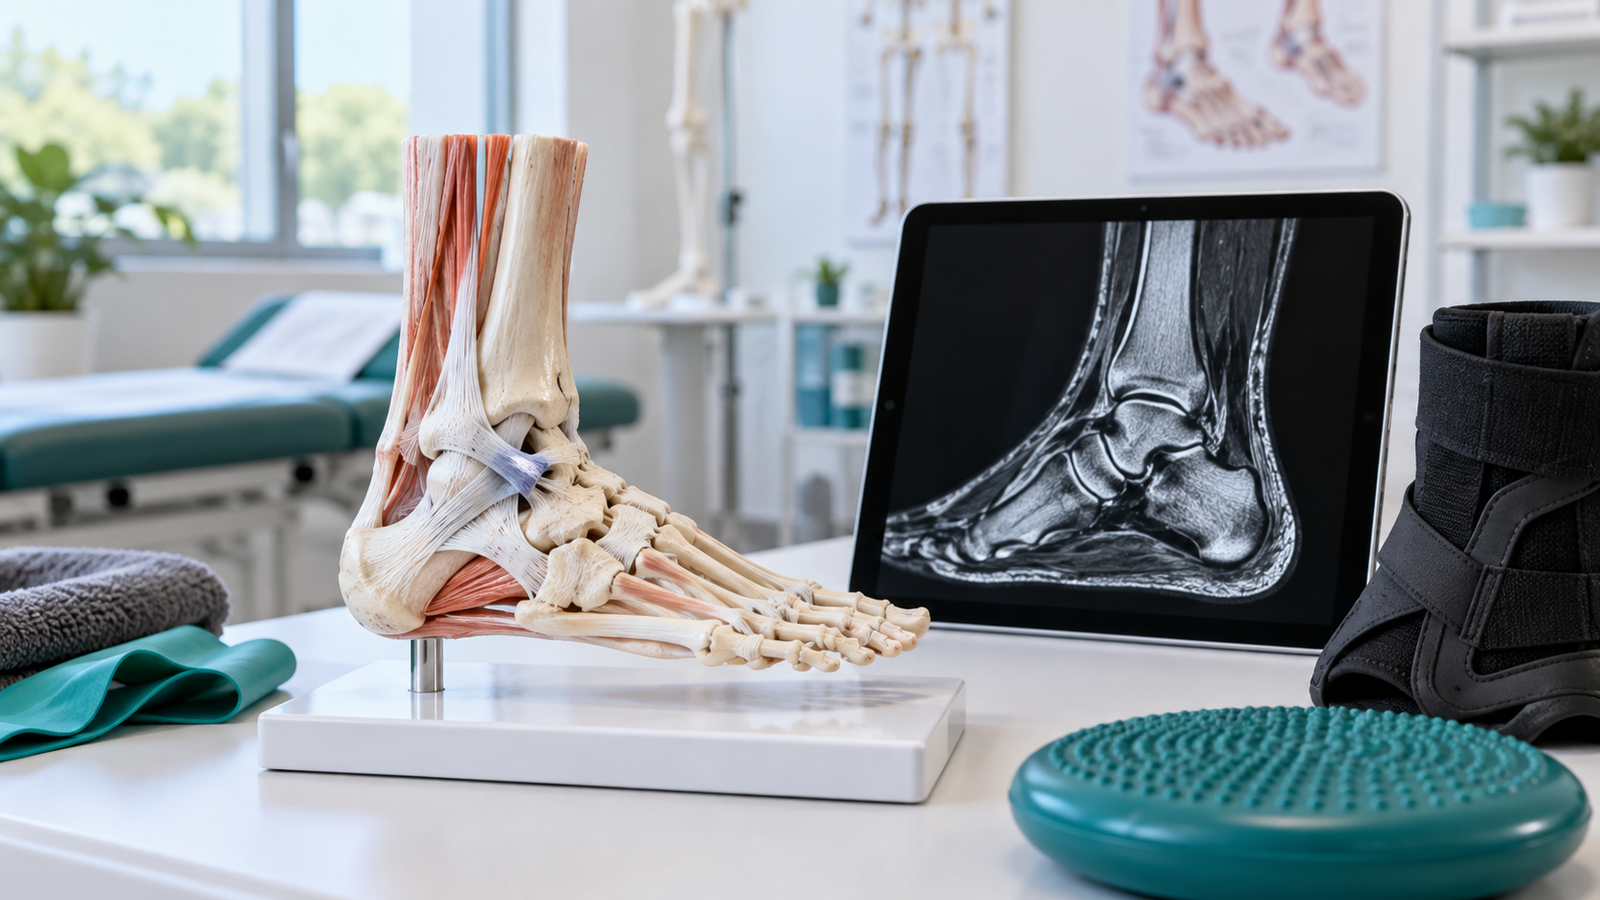
An ankle that repeatedly rolls on uneven ground is not always simply a “weak ankle.” After one or more lateral ankle sprains, the injured ligaments and the joint's balance system may not fully recover. The result can be chronic ankle instability: recurrent sprains, swelling after activity, reduced confidence, or a feeling that the ankle suddenly gives way.
The anterior talofibular ligament, commonly called the ATFL, is often the first lateral ligament injured when the foot turns inward. Many ATFL injuries heal with appropriate protection and rehabilitation. Specialist review becomes important when instability continues, when sprains keep recurring, or when pain suggests that cartilage, tendons, another ligament, or bone may also be involved.
What does the ATFL do?
The ATFL connects the outer ankle bone, or fibula, to the talus. It helps control forward movement and inward rotation of the talus within the ankle joint. During a typical inversion sprain, the foot rolls inward while the ankle is pointed down, placing the ATFL under sudden tension.
A mild sprain stretches ligament fibres, while a more serious injury can partially or completely tear them. The calcaneofibular ligament may also be injured in a stronger sprain. The severity of pain on day one does not by itself show whether the ankle will later remain stable; recovery also depends on swelling control, movement, strength, balance, alignment, and return-to-sport progression.
How a first sprain can become repeated instability
After an ankle sprain, pain and swelling can alter the way a person walks and reduce ankle movement. The muscles that resist inward rolling may become weaker or react more slowly. Joint-position awareness, known as proprioception, can also be impaired. Returning to sport as soon as pain settles, without rebuilding these functions, leaves the ankle vulnerable during landing, cutting, or an unexpected step.
Repeated injuries may stretch already damaged ligaments and create mechanical laxity. Other patients have little measurable looseness but still feel unstable because balance, muscular control, and confidence have not recovered. Chronic ankle instability can therefore include both a structural ligament problem and a functional control problem, and treatment should identify which factors are present.
Symptoms that suggest more than a routine sprain
A new sprain normally causes pain, tenderness, bruising, and swelling. Persistent instability has a different pattern. The ankle may give way while walking on uneven ground, descending stairs, turning quickly, or playing sport. Some people describe repeated minor rolls that no longer cause dramatic bruising but continue to interrupt activity.
Other warning signs include swelling after every game or long walk, pain around the outer ankle, reduced range of motion, difficulty balancing on one leg, or reliance on a brace for ordinary activity. Deep joint pain, catching, or locking may indicate cartilage injury. Pain behind the fibula can involve the peroneal tendons, while tenderness directly over bone needs assessment for a possible fracture.
When should you seek specialist care?
Prompt assessment is advisable after a severe injury if you cannot bear weight, the ankle looks deformed, pain is directly over a bone, swelling is rapidly increasing, or the foot becomes numb, pale, or unusually cold. A severe sprain can resemble a fracture and should not be diagnosed from appearance alone.
For a less urgent injury, arrange review when pain and swelling are not steadily improving, when the ankle repeatedly gives way, or when you cannot return to normal work or sport despite rehabilitation. A history of several sprains deserves evaluation even if the ankle feels comfortable between episodes. Dr Rahul Grover's ankle ATFL injury service explains the focused assessment and treatment pathway.
How chronic ankle instability is diagnosed
Diagnosis starts with the story of the first injury, the number of repeat sprains, treatment already completed, and the movements that trigger giving way. The examination compares both ankles for swelling, tenderness, movement, strength, balance, foot alignment, and ligament stability. Tests such as the anterior drawer and talar tilt help assess lateral ligament laxity.
X-rays may be used to look for fracture, alignment problems, loose bone fragments, or signs of joint damage. Stress X-rays can help assess instability in selected cases. MRI is not automatically needed for every sprain, but it can be useful when symptoms persist, surgery is being considered, or an associated cartilage, tendon, or ligament injury is suspected. Ultrasound may provide dynamic assessment of superficial ligaments and tendons when clinically appropriate.
Rehabilitation remains the first-line treatment
Most isolated lateral ankle sprains are treated without surgery, including many complete tears. Early care may involve short-term protection, swelling control, and supported weight-bearing according to injury severity. Prolonged immobilisation without a clear indication can leave the joint stiff and muscles deconditioned, so rehabilitation usually begins as soon as it is safe.
A structured programme restores ankle movement, calf and peroneal strength, and control of the foot during weight-bearing. Balance work progresses from stable double-leg tasks to single-leg control, unstable surfaces, reaching, landing, hopping, and direction changes. The exercise must eventually resemble the person's sport or work; being able to stand on one leg is not the same as controlling the ankle during a fast cut.
Bracing or taping may reduce the chance of another sprain during early return to activity. It supports the programme but does not replace strength and proprioception training. Footwear, training load, playing surface, and movement technique may also need attention through a broader sports injury assessment.
Why symptoms can continue despite exercises
Rehabilitation may appear to fail when it was too short, progressed too slowly, or never included sport-specific landing and change-of-direction work. Persistent symptoms can also come from a missed associated injury. Osteochondral lesions of the talus, ankle impingement, peroneal tendon problems, syndesmotic injury, subtalar instability, or an old avulsion fracture may imitate or accompany ATFL instability.
This is why repeating the same home exercises indefinitely is not always the answer. A specialist can reconsider the diagnosis, review the quality and duration of rehabilitation, and decide whether additional imaging or a modified programme is appropriate.
When does ATFL injury need surgery?
Surgery is not based on an MRI report alone. It may be considered when recurrent giving way and objective instability continue after a well-supervised period of rehabilitation, especially when the problem limits sport, work, or daily activity. The decision also considers ligament quality, foot alignment, generalised laxity, previous operations, associated joint damage, and the patient's goals.
An anatomical lateral ligament repair, often based on the Brostrom technique, tightens and reattaches the damaged ligament tissue. Reconstruction with a graft may be required when the native tissue is inadequate or instability is more complex. Arthroscopy may be combined with stabilisation when examination and imaging identify cartilage injury, impingement, or loose tissue inside the joint.
Recovery after surgery still requires protection followed by staged movement, strengthening, balance training, and sport-specific progression. Surgery restores stability; rehabilitation teaches the leg to use that stability safely.
Returning to running and sport safely
Return should be based on function rather than a calendar date. Pain and swelling should be controlled, ankle movement should be useful, and strength should approach the uninjured side. The athlete should demonstrate single-leg balance, repeated heel raises, hopping, landing, acceleration, and planned and reactive direction changes without giving way.
Training usually resumes in stages: straight-line activity, faster running, controlled cutting, non-contact practice, and then full participation. A brace may be used during higher-risk activity for a period advised by the treating team. Any increase in swelling or instability after a progression is a reason to review the load rather than push through it.
How Dr Rahul Grover plans ankle instability care
Dr Rahul Grover evaluates repeated ankle sprains by separating pain from true instability and identifying mechanical, neuromuscular, alignment, and activity-related contributors. The plan may include targeted rehabilitation, activity modification, bracing, selective imaging, and regular functional review.
When symptoms continue despite appropriate care, surgical repair or reconstruction is discussed according to the ligament injury and any associated ankle problem. The aim is not only to stop the ankle rolling but to restore confidence, movement quality, and a durable return to work or sport.
Conclusion
Repeated ankle sprains should not be accepted as inevitable. An injured ATFL can leave structural looseness, impaired balance, or both, while cartilage and tendon injuries may add persistent pain. Most patients improve with accurate diagnosis and a progressive rehabilitation programme, but recurrent giving way after proper treatment deserves specialist review.
Early attention to movement, strength, proprioception, and return-to-sport testing can interrupt the cycle of repeated injury. When those measures are not enough, carefully selected ligament repair or reconstruction may provide the stability needed for confident activity.

About Dr Rahul Grover
Dr. Rahul Grover is a highly respected orthopaedic surgeon known for advanced joint replacement, arthroscopy, spine care, fracture management, and sports orthopaedics.
Know More