Bone Tumor Warning Signs: When Persistent Bone Pain Should Not Be Ignored
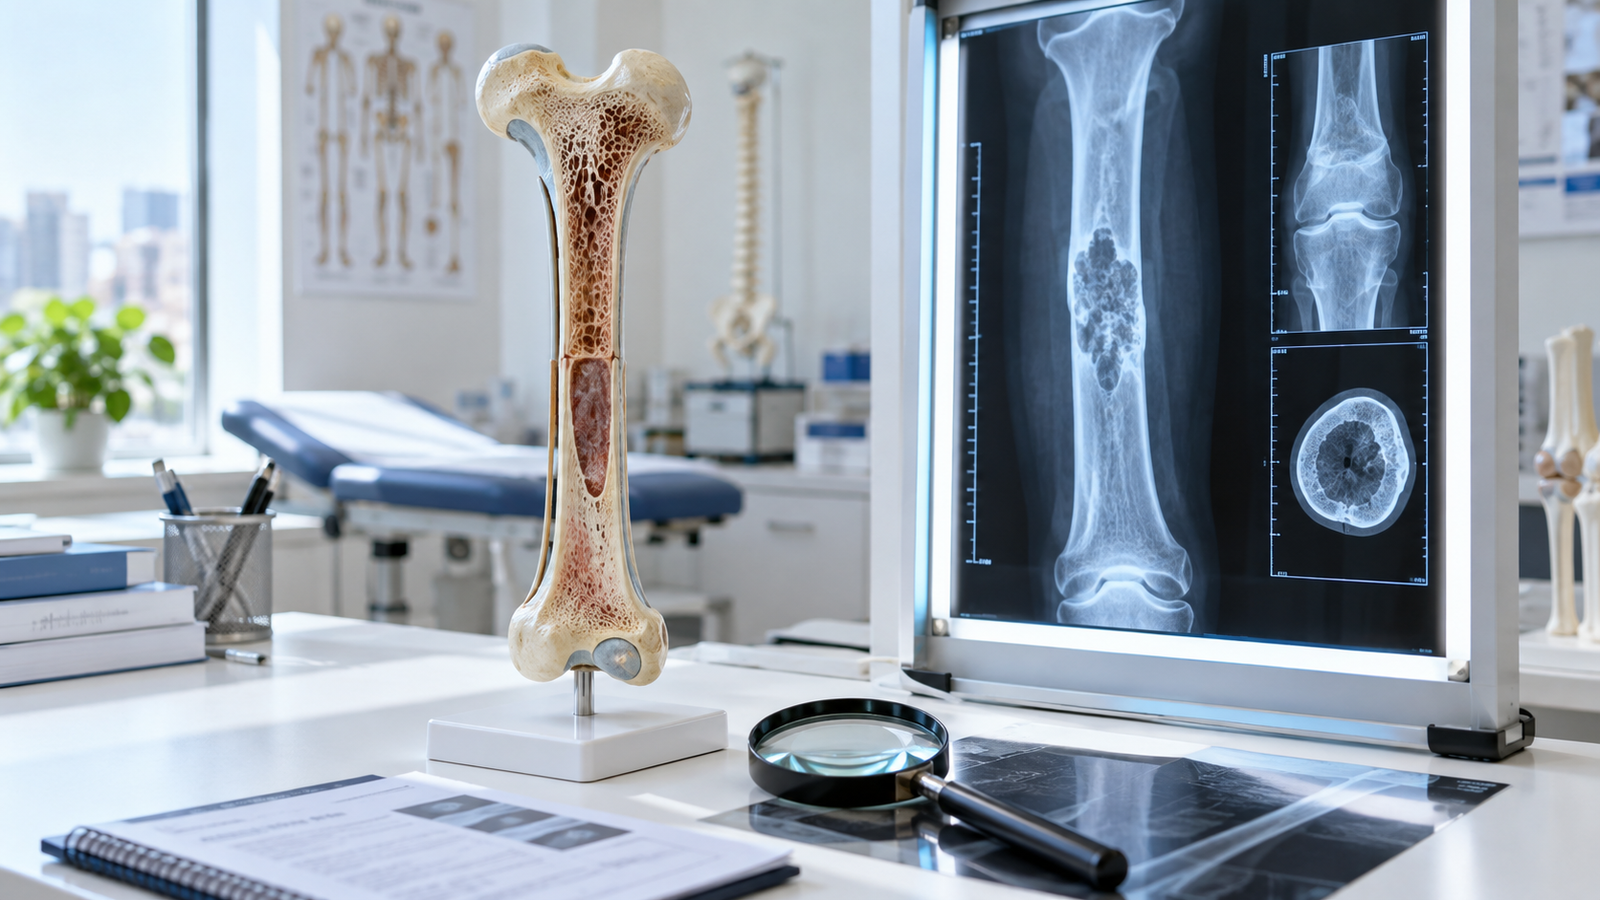
Bone pain is common and is usually caused by an injury, overuse, arthritis, infection, or another non-cancerous condition. A persistent ache does not automatically mean that a person has a bone tumor. However, pain that continues without a clear reason, gradually worsens, occurs at rest or at night, or appears with swelling deserves a proper medical assessment.
Bone tumors include a wide range of conditions. Many are benign and never spread to another part of the body. Some benign lesions still weaken bone or affect a nearby joint, while primary malignant bone tumors are rare but need timely specialist care. The goal of evaluation is not to create alarm; it is to identify the cause accurately and avoid overlooking a lesion that requires monitoring or treatment.
What is a bone tumor?
A bone tumor is an abnormal growth of cells within or on the surface of a bone. Benign tumors can remain stable, grow slowly, or occasionally behave aggressively in their local area. Malignant primary bone tumors begin in bone tissue. These are different from secondary, or metastatic, tumors that begin in another organ and later spread to bone.
The type of lesion cannot be decided from pain alone. Age, the bone involved, the exact location within that bone, X-ray appearance, growth pattern, and associated symptoms all matter. Some harmless lesions are found by chance on an X-ray taken after an injury, while a more important lesion may initially resemble a sports strain or ordinary joint pain.
Persistent or progressive bone pain
The most important signal is a change from the expected pattern. Pain from a minor strain should generally improve as the tissue heals. Bone pain that lasts, becomes more frequent, increases in intensity, or returns despite appropriate rest and treatment needs review. Pain may be felt as a deep ache and may not be limited to movement.
Night pain can be a warning sign when it repeatedly wakes a person, is present even in a comfortable position, or is becoming progressively worse. Yet night pain is not specific to cancer; arthritis, inflammation, stress injury, and infection can also cause it. The persistence and progression of symptoms, rather than one isolated feature, guide the need for investigation.
Swelling, a lump, or warmth over a bone
A new lump or swelling over an arm, leg, chest wall, pelvis, or another bone should be examined, particularly if it is enlarging. Swelling may appear later than pain and can be difficult to notice when a lesion lies deep beneath muscle. The area may feel tender or warmer than the surrounding tissue.
Not every lump is a tumor, and not every tumor is malignant. Cysts, old injuries, infection, and soft-tissue conditions may produce similar findings. Assessment is still important because examination and imaging help determine whether the swelling arises from bone, a joint, muscle, or another structure.
Difficulty moving, limping, or reduced function
A lesion near a joint may cause stiffness, reduced movement, or pain during daily activity. A child may begin limping or avoid sport; an adult may notice increasing difficulty climbing stairs, lifting an arm, or bearing weight. These changes can be mistaken for a sprain or arthritis when there was no clear injury.
Persistent functional decline matters even when pain is modest. Comparing both limbs, examining the adjacent joint, and checking muscle strength can reveal whether the problem behaves like a routine joint condition or needs bone-focused imaging.
A fracture after little or no trauma
Some tumors and tumor-like lesions reduce the strength of bone. A fracture may then occur after a minor fall, simple twist, or normal activity that would not usually break healthy bone. This is called a pathological fracture. Osteoporosis and other metabolic conditions can also cause low-impact fractures, so the cause must be investigated rather than assumed.
An unexpected fracture needs careful imaging of the entire abnormal area before definitive treatment is planned. The fracture and the underlying lesion may need to be managed together. Dr Rahul Grover's fracture surgery service describes the broader approach to complex fracture assessment and fixation.
General symptoms and medical history
Unexplained fever, marked fatigue, or weight loss can occur with many medical conditions and are less common signs of primary bone cancer. Their importance increases when they accompany persistent focal bone pain, swelling, or a lump. A previous cancer diagnosis is also relevant because several cancers can spread to bone.
Tell the clinician about earlier cancers, radiotherapy, known bone conditions, recent infections, family history, and all current symptoms. A person with a history of cancer should report new persistent bone pain to the team responsible for follow-up, even if routine appointments are months away.
Bone pain in children and teenagers
Children commonly experience minor injuries and short-lived aches, but persistent localised pain should not automatically be labelled as growing pain. Pain in one specific area, swelling, a limp, reduced activity, or symptoms that repeatedly disturb sleep deserve examination.
The clinician considers injury, infection, inflammatory disease, stress fracture, benign lesions, and the rare possibility of a malignant tumor. Early evaluation is especially useful when a child cannot explain a clear injury or symptoms are becoming more noticeable over time.
How a suspicious bone lesion is evaluated
The process begins with a focused history and physical examination. The doctor identifies the exact point of pain, checks for swelling or a mass, examines the nearby joint, and assesses movement, strength, nerves, circulation, and walking pattern. The first imaging test is often a plain X-ray because it can show the lesion's location, margins, effect on the bone, and any fracture.
MRI can define the lesion inside the bone and its relationship to muscles, nerves, vessels, and the nearby joint. CT can provide additional detail about the bone structure, while other scans may be used when the diagnosis or staging requires them. Blood tests can support the assessment but cannot by themselves confirm or exclude most bone tumors.
Why biopsy planning matters
A biopsy removes a small tissue sample for laboratory diagnosis. It is not required for every bone lesion; some have a characteristic benign appearance and can be monitored. When biopsy is needed, the route should be planned by the team that would perform definitive treatment because a poorly placed biopsy track can complicate later surgery.
Imaging is therefore reviewed before biopsy, not as an afterthought. Patients should avoid arranging an unplanned procedure solely because a report uses words such as lesion, cyst, or tumor. The bone tumor surgery and evaluation service explains this diagnosis-first approach.
Do all bone tumors need surgery?
No. A small, symptom-free benign lesion may only need periodic clinical and imaging review. Other benign tumors require treatment because they are painful, growing, weakening the bone, or affecting movement. Options can include curettage, excision, bone grafting or cement, and internal fixation when structural support is needed.
A malignant or aggressive lesion requires multidisciplinary planning based on its exact pathology, size, location, and stage. Treatment may combine surgery with chemotherapy, radiotherapy, or other specialist care. Decisions should follow a confirmed diagnosis rather than assumptions made from symptoms or a single scan.
When should you arrange an appointment?
Book an orthopaedic assessment for bone pain that is persistent, unexplained, progressively worsening, or repeatedly present at night. Seek review for a growing lump, focal swelling, unexplained limp, reduced joint movement, or an abnormality reported on an X-ray. A low-impact fracture also requires investigation of bone quality and any underlying lesion.
Urgent assessment is appropriate when severe pain follows a minor event and a fracture is possible, swelling grows rapidly, the limb becomes weak or numb, or fever accompanies severe local pain and illness. These symptoms can have several causes, including infection, and should not wait for routine self-care.
How Dr Rahul Grover approaches bone lesion care
Dr Rahul Grover reviews the symptom pattern, examination findings, and complete imaging rather than treating the word "tumor" as a diagnosis. Previous X-rays are valuable because comparison can show whether a lesion is stable or changing. MRI, CT, laboratory tests, or specialist biopsy planning are advised only when they add useful information.
Treatment focuses on the exact diagnosis, fracture risk, pain, function, and preservation of the nearby joint. Patients with complex or malignant conditions are guided toward coordinated multidisciplinary care, while benign lesions are monitored or treated according to their behaviour.
Conclusion
Most bone pain is not caused by a tumor, and many bone tumors are benign. The features that should not be ignored are persistence, progression, rest or night pain, swelling, a growing lump, declining movement, or a fracture after minimal trauma. These signs do not prove cancer, but they justify evaluation.
A clear sequence of examination, X-ray, selective advanced imaging, and properly planned biopsy can prevent both delay and unnecessary procedures. If bone pain is not following the expected course, finding the reason is more useful than continuing to wait or repeatedly treating the symptom alone.

About Dr Rahul Grover
Dr. Rahul Grover is a highly respected orthopaedic surgeon known for advanced joint replacement, arthroscopy, spine care, fracture management, and sports orthopaedics.
Know More